
 close


 LOGIN
You are viewing 1 of your 1 free articles
GLP-1 in Sports: Medical Breakthrough, Performance Tool, or Emerging Risk?
GLP-1-based drugs continue to grab the attention of the global health industry and have naturally seeped into sports medicine. Candice MacMillan unpacks what we know so far and possible considerations for athletes and clinicians.



Serena Williams of the U.S. in action during her first round match against Australia’s Maya Joint REUTERS/Toby Melville
When Serena Williams disclosed in 2025 that she was using tirzepatide (Zepbound) after struggling to lose weight following her second pregnancy, the story attracted attention beyond medicine. She emphasized that the treatment complemented, not replaced, training and healthy eating, while also acknowledging a commercial partnership with the prescribing platform. In June 2026, Williams returned to professional tennis after 1,375 days and won her first doubles match. Her return is compelling, but it does not provide evidence that GLP-1-based drugs enhance performance. However, it raises an important question in the sporting arena: when a legitimate metabolic treatment changes body mass, appetite, and fueling capacity, what does that mean for athletes’ health, performance, and fair play?
What are GLP-1 Drugs?
Glucagon-like peptide-1 (GLP-1) is a hormone released from the gut after food intake. It helps regulate blood glucose levels by increasing glucose-dependent insulin secretion, reducing glucagon release, slowing gastric emptying, and signaling satiety in the brain. GLP-1 receptor agonists mimic these effects but are engineered to last much longer than natural GLP-1.
Semaglutide (Ozempic/Wegovy) and liraglutide (Victoza/Saxenda) act on GLP-1 receptors. Tirzepatide (Mounjaro/Zepbound), often discussed alongside these drugs, is technically a dual glucose-dependent insulinotropic polypeptide (GIP)/GLP-1 receptor agonist. These medicines are not interchangeable, and brand names do not reliably indicate clinical indications or doses.
Why Are They Prescribed?
GLP-1-based medicines were developed principally for type two diabetes and obesity, which are chronic diseases with substantial cardiovascular and metabolic consequences. Depending on the product and the regulator, approved indications now also include chronic weight management; reduction of major cardiovascular events in selected adults with cardiovascular disease and overweight or obesity; and, for tirzepatide, moderate-to-severe obstructive sleep apnea in adults with obesity.
“This distinction matters in sport.”
This distinction matters in sport. Athletes with type two diabetes or clinically significant obesity may have a sound medical indication and experience better glycemic control, lower cardiometabolic risk, and improved capacity to train. Prescribed treatments should not be automatically equated with cosmetic use or doping. Conversely, obtaining a drug without a proper assessment simply to “make weight” is a very different and potentially hazardous scenario.
Why Might Athletes be Interested?
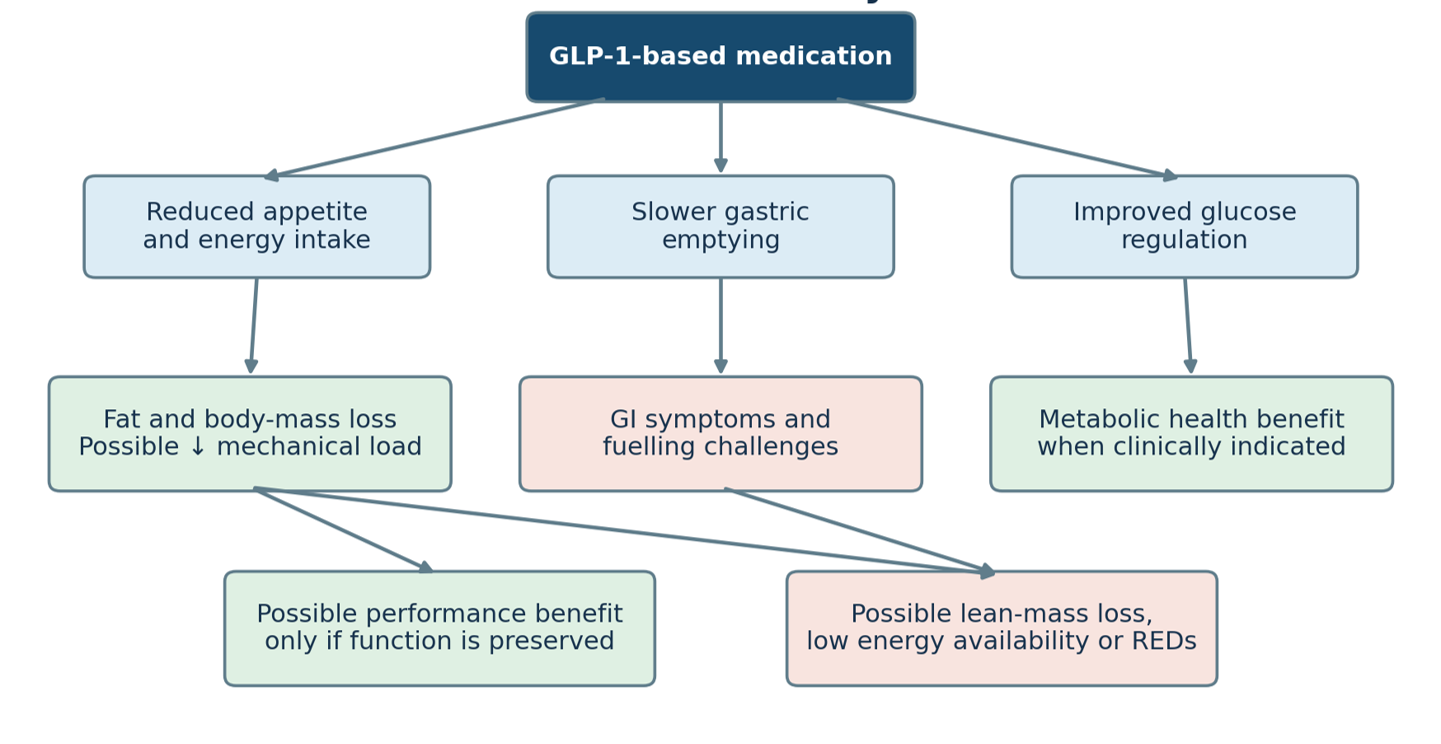
Lower fat mass may reduce mechanical loading and improve the ratio between force or power and body mass in some sports. This creates an obvious interest in endurance, jumping, aesthetic, and weight-category sports. Appetite suppression may also make weight management easier.
However, a lighter athlete is not necessarily faster, stronger, or healthier. Most GLP-1 research has involved adults with obesity and/or diabetes, not healthy, highly trained competitors. Currently, there is no convincing direct evidence that these drugs improve athletes’ competitive performance. Therefore, extrapolating clinical weight-loss results to elite sports is scientifically unsafe. Although research on this topic is limited, the potential effects of GLP-1 drugs on athletes are multi-factorial (see figure 1).
Weight Loss and Improving Performance
The relevant question is not only “How much weight was lost?” but “What tissue was lost, and what happened to performance?” A 2024 network meta-analysis of 22 randomized trials found that GLP-1-based treatments reduced fat mass but also reduced lean mass; approximately 25% of total weight loss was lean tissue(1).
The athlete should not interpret this to mean that 25% of the weight loss is necessarily contractile muscle, because DXA-derived lean mass includes body water and non-fat tissues. Nevertheless, the signal is important for this study. In a STEP 1 substudy, semaglutide reduced body mass by 15.0%, fat mass by 19.3%, and lean mass by 9.7% over 68 weeks(2). In the SURMOUNT-1 substudy, tirzepatide reduced body mass by 21.3%, fat mass by 33.9%, and lean mass by 10.9% over 72 weeks(3). Both studies involved people with overweight or obesity, not athletes, and neither established the consequences for sprinting, strength, power, repeated high-intensity efforts, or injury risk.
A better fat-to-lean ratio may be advantageous only if muscle function, training quality, and recovery are preserved (see table 1). Rapid weight loss accompanied by reduced force production, depleted glycogen stores, or limited training availability may worsen rather than improve performance.
Table 1: Potential benefit versus practical concerns of GLP-1 use in athletes
| Potential benefit | Critical qualification |
| Reduced fat and total body mass | Some lost mass may be lean tissue; function must be measured. |
| Improved glycemic and cardiometabolic health | Most relevant when a genuine metabolic indication exists. |
| Reduced mechanical loading | Rapid loss may compromise tissue capacity, strength, and recovery. |
| Improved power-to-weight ratio | Only if force, power, glycogen availability, and training quality are preserved. |
| Lower appetite and fewer cravings | May prevent adequate energy, carbohydrate, protein and fluid intake. |
| Easier weight-category management | Could enable unsafe rapid loss, secrecy, or disordered eating. |
The Athlete-Specific Risks
Nausea, vomiting, diarrhea, constipation, abdominal discomfort, and delayed gastric emptying are well-recognized adverse effects. In daily life, these may be manageable; however, during heat exposure, travel, double training sessions, or competition, they can disrupt carbohydrate delivery, hydration, and recovery. Hypoglycemia is usually uncommon when these agents are used alone, but the risk changes when they are combined with insulin or insulin secretagogues.
A deeper concern is chronic under-fueling. Athletes whose hunger is markedly reduced may struggle to consume sufficient total energy, carbohydrates, and protein. Low energy availability can impair endocrine and reproductive function, bone health, immunity, protein synthesis, cardiovascular health, and psychological well-being while compromising training response and performance. In susceptible athletes, this may contribute to Relative Energy Deficiency in Sport (REDs)(4). Weight-category and aesthetic sports increase the risk of rapid loss, disordered eating, and secrecy.
Product-specific contraindications and warnings are also important. These include severe gastrointestinal reactions, gallbladder disease, pancreatitis signals, kidney injury secondary to dehydration, and contraindications related to medullary thyroid carcinoma or multiple endocrine neoplasia type two. A drug that is appropriate for one athlete may be unsuitable for another athlete.
Managing Risks
Where a genuine clinical indication exists, management should be integrated rather than left to the prescriber. Sports physicians and dietitians should establish baseline health, medication, and eating disorder history; monitor gastrointestinal symptoms, hydration, and weight loss rate; and track body composition alongside strength, power, training quality, recovery, injuries, menstrual function, and other REDs indicators.
Resistance training and adequate protein intake are rational strategies to protect lean tissue, although specific trials in athletes taking GLP-1 drugs are lacking(5). In adults with obesity, supervised exercise combined with liraglutide produced greater improvements in body fat percentage and cardiorespiratory fitness than either approach alone(6). This supports exercise as an essential companion to treatment, not as proof of an ergogenic drug effect.
“A deeper concern is chronic under-fueling.”
Practically, athletes may need smaller, more frequent meals; deliberate carbohydrate intake before and during demanding sessions; protein distributed throughout the day; and an individual hydration plan. Dose escalation and competition schedules should be coordinated with the treating clinicians. Persistent vomiting, inability to fuel, rapid functional decline, or emerging REDs features should prompt a prompt reassessment.
Permitted, but Watched, by WADA
GLP-1 receptor agonists are not prohibited under the 2026 World Anti-Doping Agency (WADA) Prohibited List. Semaglutide and markers of other GLP-1 analogs are included in the 2026 monitoring program(7). Monitoring is surveillance; i.e., detection does not constitute an anti-doping rule violation.
.
WADA may prohibit a substance if it meets at least two of the following three criteria: potential to enhance performance, actual or potential health risk, and violation of the spirit of sport(8). The case for prohibition is that GLP-1 drugs could facilitate aggressive weight manipulation, provide an advantage in weight-sensitive sports, and carry health risks when misused. The counterargument is stronger at present: there is no robust evidence of direct performance enhancement in healthy athletes; the appetite and lean mass effects may impair performance; and athletes may have legitimate medical indications.
Questions before an athlete uses a GLP-1-based drug
• Is there a clear, documented clinical indication?
• Who prescribes the drug and coordinates it with the sports medicine team?
• Are body composition, strength, power, and training quality being monitored, in addition to body weight?
• Can athletes still meet their energy, carbohydrate, protein, and hydration requirements?
• Are gastrointestinal symptoms interfering with training, travel, or competition?
• Are menstrual function, bone health, mood, recovery, or injury patterns changing?
• Has the exact medication been checked against the current WADA list?
Based on current evidence, targeted monitoring, education, and medical oversight are more defensible than a blanket ban. This position should remain open to revision as athlete-specific prevalence, performance, and safety data emerge. Athletes must still check the exact product before use, as formulations and anti-doping rules can change.
“GLP-1 receptor agonists are not prohibited...”
The Final Whistle
GLP-1-based drugs are powerful medicines that are not simple appetite suppressants or proven performance enhancers. They may improve health and training capacity in athletes with a valid clinical indication, but intentional weight loss can include lean tissue, and appetite suppression may undermine the fueling on which performance depends. The key sporting principle is therefore not “lighter is better,” but “health, function, and performance must be protected.” Use should be medically justified, openly coordinated with the sports medicine team, and monitored beyond the scale reading.
References
1. Metabolism. 2025;164:156113.
2. J Endocr Soc. 2021;5(Suppl 1):A16-A17.
3. Diabetes Obes Metab. 2025;27:2720-2729.
4. Br J Sports Med. 2023;57:1073-1097.
5. Diabetes Care. 2024;47:1718-1730.
6. N Engl J Med. 2021;384:1719-1730.
7. World Anti-Doping Agency. The 2026 Monitoring Program. 2025.
8. World Anti-Doping Agency. The Prohibited List: criteria for including substances and methods.

Candice MacMillan

Latest Issue

Subscribe Today
Newsletter Sign Up
Subscriber Testimonials
Dr. Alexandra Fandetti-Robin, Back & Body Chiropractic
Elspeth Cowell MSCh DpodM SRCh HCPC reg
William Hunter, Nuffield Health
Subscribe Today




Newsletter Sign Up
Coaches Testimonials
Dr. Alexandra Fandetti-Robin, Back & Body Chiropractic
Elspeth Cowell MSCh DpodM SRCh HCPC reg
William Hunter, Nuffield Health
Subscribe Today
Latest Issue

Be at the leading edge of sports injury management
Our international team of qualified experts (see above) spend hours poring over scores of technical journals and medical papers that even the most interested professionals don't have time to read.
For 17 years, we've helped hard-working physiotherapists and sports professionals like you, overwhelmed by the vast amount of new research, bring science to their treatment. Sports Injury Bulletin is the ideal resource for practitioners too busy to cull through all the monthly journals to find meaningful and applicable studies.
*includes 3 coaching manuals
Get Inspired
All the latest techniques and approaches


Sports Injury Bulletin brings together a worldwide panel of experts – including physiotherapists, doctors, researchers and sports scientists. Together we deliver everything you need to help your clients avoid – or recover as quickly as possible from – injuries.
We strip away the scientific jargon and deliver you easy-to-follow training exercises, nutrition tips, psychological strategies and recovery programmes and exercises in plain English.
