
 close


 LOGIN
You are viewing 1 of your 1 free articles
From Control to Chaos: Tibia-Fibular Fracture
Eurico Marques explores how to manage the return of athletes to play after a tibia–fibula fracture and what the control–chaos continuum offers every practitioner.



LAFC forward Son Heung-Min controls the ball during the first half against Sporting Kansas City at BMO Stadium. Mandatory Credit: Kiyoshi Mio-Imagn Images
A broken tibia and fibula is one of the most dramatic injuries an athlete can suffer. Rebuilding a player to survive and then perform in the chaos of competition takes far more than waiting for bone to heal. This article unpacks a published Premier League case and the control–chaos continuum framework underpinning it, and distills the principles any clinician can apply.
A Rare Injury
Traumatic fracture is mercifully rare in football, but contact, a poorly timed challenge, can snap both the tibia and fibula(1,2). When it does, it tests every layer of the rehabilitation process: tissue healing, load progression, physical preparation, and communication. The medical and performance team at an English Premier League club documented one such case in the journal BMJ Open Sport & Exercise Medicine: an open distal tibia–fibula fracture in a first-team player, managed all the way back to competitive match play(1). The player returned to full team training at 7.5 months, completed 90 minutes of match play at nine months, and remained injury-free 11 months after returning to sport.
What makes the report valuable is not the timeline but the target it identifies. The temptation after a fracture is to make the early phase all about radiology and the late phase all about running. The real target sits between the two: restoring the limb’s capacity to absorb and produce force well enough that running, changing direction, striking, tackling, and reacting can all be layered back in without exceeding tissue tolerance. The return to sports is chaotic.
“The return to sports is chaotic.”
The Right to Run
The central message of the case is blunt: progressive mechanical loading is the foundation for return to running after a traumatic fracture(1). Bone is a living tissue that adapts to the loads placed on it, and it needs the right kind of stimulus (dynamic, varied, and progressive) to remodel and regain stiffness(3-5). Early management aims to minimize atrophy, restore pain-free range of motion, and apply load that would stimulate healing rather than threaten it. In plain terms, the limb has to become load-worthy.
This is where strength training is essential. A progressive program should combine isometrics, building force in the key running positions around acceleration and stance, with progressive dynamic hip and knee strength work, blood-flow-restriction training in selected exercises to drive adaptation at lower mechanical loads, and a graded jump-landing sequence that bridges the gap between strength and high-rate force acceptance(6). By the time clinicians would like to reintroduce running, the player should have the physical qualities to withstand the running demands, rather than simply resting the fracture into healing.
Clinicians must use objective measures to support their decision-making. There should be physiological fracture site healing (on imaging), and isometric strength should be less than 10% peak-force asymmetry between limbs. That combination, not the timeframe, justifies progression to an anti-gravity treadmill, starting at 60% of body weight and building to 90% before transitioning to grass. Time alone should never drive these decisions; clinicians must consider imaging, symptoms, force qualities, and function.
The Early Timeline
- Weeks 0–3: surgical fixation, soft-tissue and swelling management, elevation and early range of motion.
- Weeks 3–6: full weight-bearing with near-normal gait, improving ankle dorsiflexion, and progression from double-leg to single-leg gym work.
- Weeks 12–15: callus formation improving, bike conditioning established, isometric asymmetry under 10%, and the athlete ready for offloaded running.
The Control–Chaos Continuum
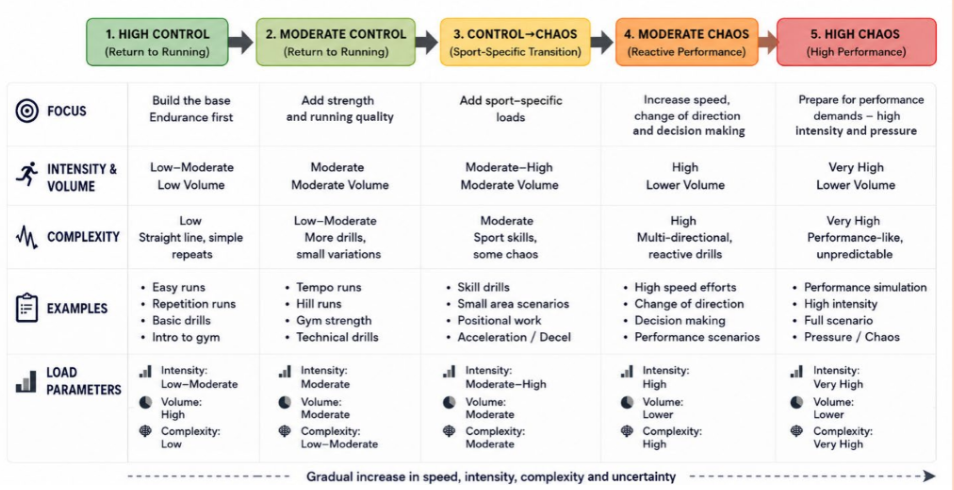
Once running tolerance is being rebuilt, clinicians must consider how to progress the athletes from straight-line jogging to the reactive physical capacity without placing the athlete at any undue risk. The authors used the control–chaos continuum (CCC), a framework first described in the British Journal of Sports Medicine that progresses on-pitch work from highly controlled, predictable tasks to increasingly variable, reactive and football-realistic demands (see figure 1)(7). Rather than jumping from running straight to full training, they built staged progressions, manipulating running speed, change of direction, technical actions, contact and load at every step (see table 1).
Bring Sport Back Early
One of the most useful clinical lessons hides in the moderate-control phase. Importantly, clinicians don’t have to delay sports-specific actions until the very end. They can introduce change of direction, simple technical drills, and even low-volume contact (e.g., a static block tackle) early and deliberately. This introduces low-impact sport-specific loads under controlled circumstances to start building tissue tolerance and psychological resilience while ensuring the dosage and context are tightly controlled(8). Constraining the task and the environment lets the clinicians expose the limb to sport-specific stress while keeping the demand predictable, and it is worth remembering that high-impact, varied loading generates the bone strains that drive remodeling far more effectively than steady running does(9,10). Drip-feeding technical qualities back in keeps the player progressing on the skills that matter while the tissue catches up.
“Time alone should never drive these decisions...”
Table 1: The five phases of the control–chaos continuum as applied in football.
| Phase | On-pitch emphasis | Key constraints/dose |
| High control | Rebuild running volume; box-to-box runs with walking recovery | Speed capped at ~60–65% of max to limit bone strain rate |
| Moderate control | Change of direction in dribbling lanes; short controlled passing; low-volume contact | Lower-threshold high speed running; static block tackles for site-specific loading |
| Control to chaos | Intensive/extensive conditioning; pass-and-move drills; position-specific accel/decel | Warm-ups and drills matched to the demands of each session |
| Moderate chaos | Game-like passing and movement; technical actions linked to high-speed running | Align chronic load with pre-injury levels |
| High chaos | Reactive football scenarios; rising sprint exposure | Reactive football scenarios; rising sprint exposure |
Progress Unpredictability, Not Just Volume
As the player advances, the sessions become less scripted. Passing distances grow, movement to receive becomes more dynamic, and technical actions are linked to high-speed running. Progression is governed not by whether the athlete ‘looks good,’ but by whether they can actually withstand the volumes and intensities that their sport would demand. In the final phase, clinicians can increase the chronic load above pre-injury training load, while staying below combined training-plus-match load. This ensures that the athlete can return seamlessly back into training before being considered for matches. Depending on the level of competition, coaches may allow athletes to return to competition on a graded basis once they have demonstrated the physical, psychological, tactical, and technical development needed to withstand the demands.
Let Testing Serve Reasoning
Clinicians must use data to support their reasoning, but never rely on a single number. For example, isometric posterior-chain and mid-thigh-pull tests help decide when to start running. Later, countermovement jump (CMJ) testing assesses the quality of force production and, crucially, force absorption. In the football case study, before return to training, jump height itself was still below pre-injury values, which, taken alone, might suggest incomplete recovery. But the more meaningful markers had returned to or exceeded baseline: neuromuscular efficiency, eccentric deceleration rate of force development, early concentric impulse, and inter-limb asymmetries close to zero(11).
The lesson is not that everyone needs a force platform, but that testing should answer useful questions: is the athlete coping with load? Can they generate force? Can they absorb it? Are asymmetries narrowing? Is the performance signature moving back toward normal? A readiness decision built on bone healing, strength, function, and load tolerance together is far sturdier than one built on time or a single metric(12).
“Clinicians must use data to support their reasoning...”
Clinical Implications
Most clinicians do not have an anti-gravity treadmill, daily imaging, or Premier League infrastructure, and they do not need it, because the principles apply universally. First, earn the right to run through progressive loading, not optimism. Second, do not separate rehab from sport for too long; gradually introduce and progress technical qualities back under controlled conditions. Third, progress unpredictability, not just volume. Fourth, use objective markers where possible to support clinical reasoning. Fifth, a multidisciplinary team is essential to ensuring the best possible outcome(12,13).
Return to sport after severe injury is not a cliff edge; it is a continuum. Too often, athletes step straight from protected rehabilitation into an environment that is suddenly chaotic, competitive and emotionally charged. The control–chaos continuum fills that gap with a language and a structure for moving from certainty to uncertainty in sensible steps. For a tibia–fibula fracture, bone healing is necessary. Still, the player also needs loading tolerance, aerobic fitness, repeat-acceleration ability, high-speed exposure, sprint confidence, technical sharpness and the capacity to perform under chaos. Build those layers progressively, measure them intelligently, and even a severe fracture need not mean a compromised return.
References
1. BMJ Open Sport Exerc Med. 2019;5:e000639.
2. Knee Surg Sports Traumatol Arthrosc. 1999;7:262-266.
3. Br J Sports Med. 2015;49:278-279.
4. Bone. 1998;23:399-407.
5. Crit Rev Eukaryot Gene Expr. 2009;19:319-338.
6. Br J Sports Med. 2017;51:1003-1011.
7. Br J Sports Med. 2019;53:1132-1136.
8. J Sports Sci. 1997;15:621-640.
9. J Appl Physiol. 2006;100:1441-1442.
10. Br J Sports Med. 2000;34:195-199.
11. Transl Sports Med. 2019;2:1-7.
12. Br J Sports Med. 2017;51:702-703.
13. Br J Sports Med. 2017;51:419-420.

Eurico Marques

Latest Issue

Subscribe Today
Newsletter Sign Up
Subscriber Testimonials
Dr. Alexandra Fandetti-Robin, Back & Body Chiropractic
Elspeth Cowell MSCh DpodM SRCh HCPC reg
William Hunter, Nuffield Health
Subscribe Today




Newsletter Sign Up
Coaches Testimonials
Dr. Alexandra Fandetti-Robin, Back & Body Chiropractic
Elspeth Cowell MSCh DpodM SRCh HCPC reg
William Hunter, Nuffield Health
Subscribe Today
Latest Issue

Be at the leading edge of sports injury management
Our international team of qualified experts (see above) spend hours poring over scores of technical journals and medical papers that even the most interested professionals don't have time to read.
For 17 years, we've helped hard-working physiotherapists and sports professionals like you, overwhelmed by the vast amount of new research, bring science to their treatment. Sports Injury Bulletin is the ideal resource for practitioners too busy to cull through all the monthly journals to find meaningful and applicable studies.
*includes 3 coaching manuals
Get Inspired
All the latest techniques and approaches


Sports Injury Bulletin brings together a worldwide panel of experts – including physiotherapists, doctors, researchers and sports scientists. Together we deliver everything you need to help your clients avoid – or recover as quickly as possible from – injuries.
We strip away the scientific jargon and deliver you easy-to-follow training exercises, nutrition tips, psychological strategies and recovery programmes and exercises in plain English.
