
 close


 LOGIN
Psychological Screening for Female Athletes
Cory Dugan presents a practical framework for psychological screening in semi-elite settings, built from existing tools.



England’s Alia Leat in action on the balance beam during the Women’s Team Final and Individual Qualification REUTERS/Matthew Childs
The Silent Gap
Physical screening has made meaningful inroads into semi-elite sport over the past decade. Clinicians increasingly recognize blood biomarker frameworks, cardiac screening protocols, and menstrual cycle monitoring as components of responsible athlete care. Psychological health has not kept pace. Research on collegiate athletes in the United States finds that approximately one in five experience a mental health concern, yet a national survey of collegiate departments found that fewer than half administer any formal screening instrument for such concerns(1,2). An athlete can complete a comprehensive cardiovascular and hematological screen and leave with no evaluation of the psychological domain that is, by any objective measure, equally capable of ending her season.
A shortage of evidence does not explain this gap. The relationship between psychological distress and physical performance outcomes is well documented. For example, high life-event stress is associated with an elevated risk of injury in the subsequent competitive season(3). Depression is among the high-prevalence disorders to which athletes are vulnerable, with risk heightened by sport-specific factors such as injury, overtraining, and burnout(4).
Eating disorder pathology, which is more common among female athletes, compounds iron deficiency, suppresses hormonal function, and amplifies bone stress injury risk, creating a physiological cascade that a blood panel alone cannot fully explain without the psychological context behind it(5).
The Implementation Barriers
Three barriers consistently prevent psychological screening from taking hold in semi-elite environments. The first is role uncertainty. Coaches and physiotherapists are comfortable acting on a ferritin result. They are far less comfortable initiating a conversation about psychological distress and unclear about whether doing so falls within their responsibility.
The second is stigma, both the athlete’s reluctance to disclose and the practitioner’s reluctance to ask. A qualitative study of young elite athletes conducted in Australia identified stigma as the single most important perceived barrier to seeking help, ahead of mental health literacy and previous negative experiences(6). The third barrier is the absence of a simple, validated, practically applicable framework, the equivalent of a tiered blood panel, for non-specialist use in sport settings.
The first two barriers require cultural change that no checklist resolves on its own, but a clear framework at least removes the excuse of not knowing where to start.
Connecting Psychological and Physical Screening
One of the strongest arguments for integrating psychological screening into existing athlete health programs is that the two domains are not separable. The physiological mechanisms run in both directions.
Relative Energy Deficiency in Sport (REDs) is the clearest example. Low energy availability hyperactivates the hypothalamic-pituitary-adrenal axis, elevating cortisol, while suppressing the hypothalamic-pituitary-gonadal axis, reducing estrogen and progesterone, a hormonal profile that drives both physical consequences (bone stress, iron dysregulation, immune suppression) and psychological ones (mood disturbance, cognitive impairment, disordered eating cognition)(5). An athlete presenting with low ferritin, elevated cortisol on her blood panel, and irregular menstrual cycles may already be producing a psychological signal in her biomarker data (see figure 1). Practitioners who read Parts I and II of this series are already collecting data with psychological implications. What is missing is the framework to act on it.
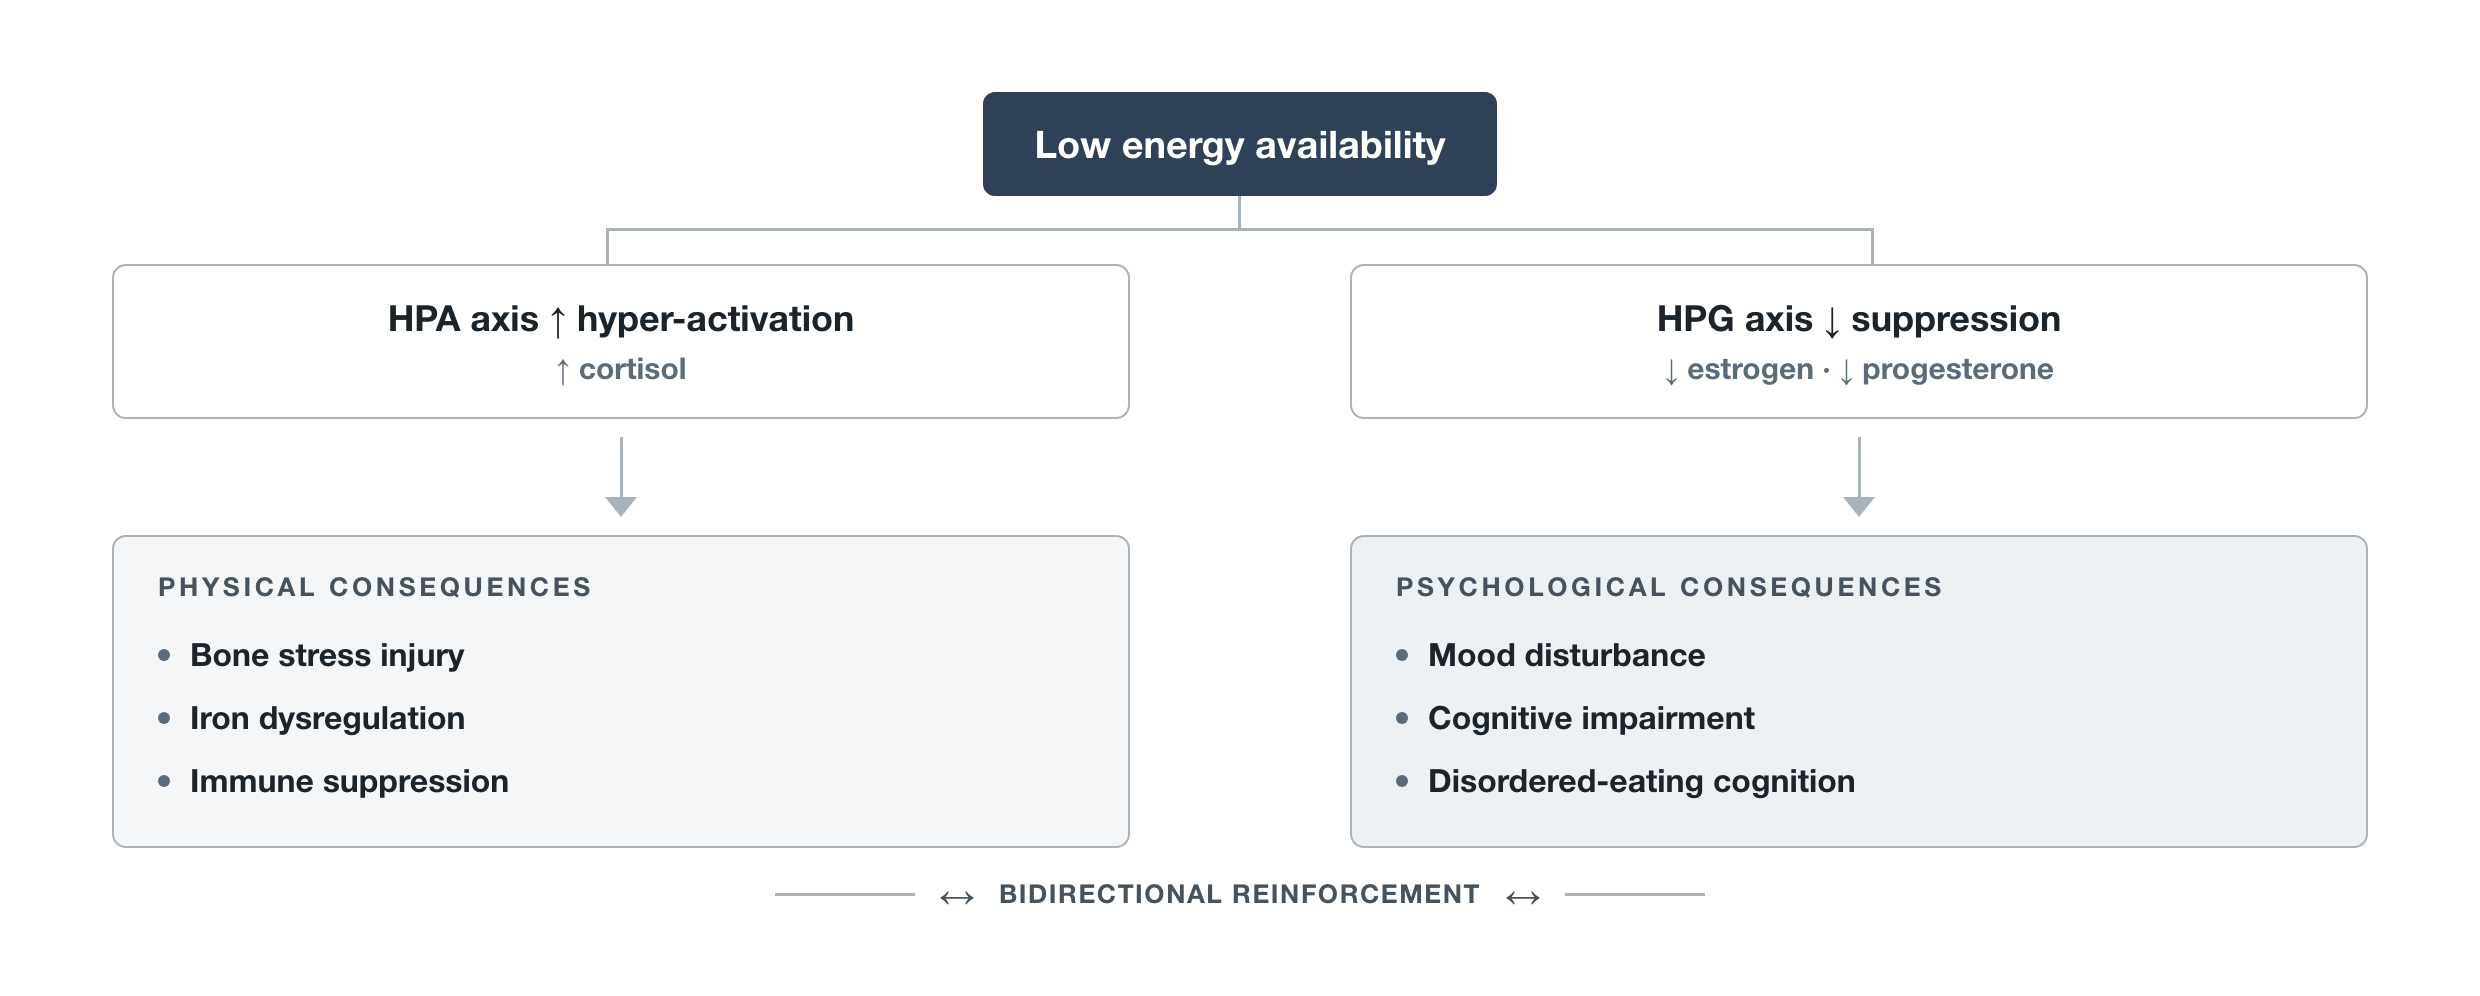
Adapted from the 2023 IOC consensus statement on Relative Energy Deficiency in Sport(5).
Sleep, which sits at the intersection of recovery monitoring and psychological health, follows the same bidirectional logic. Elite athletes are particularly susceptible to inadequate sleep, which degrades recovery and performance and is shaped in part by the same stress and anxiety that mark psychological distress(7). These effects often surface as performance decrements before appearing in any formal screen. Practitioners already tracking heart rate variability and sleep quality through wearable technology are capturing data relevant to psychological health whether they recognize it or not.
“Psychological health has not kept pace...”
The argument for integrating psychological screening is not that practitioners need to become psychologists. It is that they are already collecting data with psychological relevance, and a brief, validated instrument closes the interpretive loop.
A Practical Screening Framework
Effective psychological screening for semi-elite female athletes does not require clinical training to administer. It requires instrument selection appropriate to the setting, a clear referral pathway when results flag concern, and pre-analytic consistency, the same principles that govern blood biomarker screening. The framework is organized into two tiers, reflecting the resource and role constraints of most semi-elite environments (see figure 2).
It is worth noting that practitioners are not starting from a blank page. The International Olympic Committee’s Sport Mental Health Assessment Tool-1 (SMHAT-1) provides a validated, sport-specific tiered framework that begins with an athlete-specific screen and cascades into disorder-specific instruments, including the PHQ-9, GAD-7, and BEDA-Q, before clinical assessment(8). The two-tier approach presented here is best understood as the low-resource, non-specialist on-ramp to that model: the same logic, stripped to what a coach or physiotherapist can administer in a semi-elite setting without a sports-medicine department behind them.
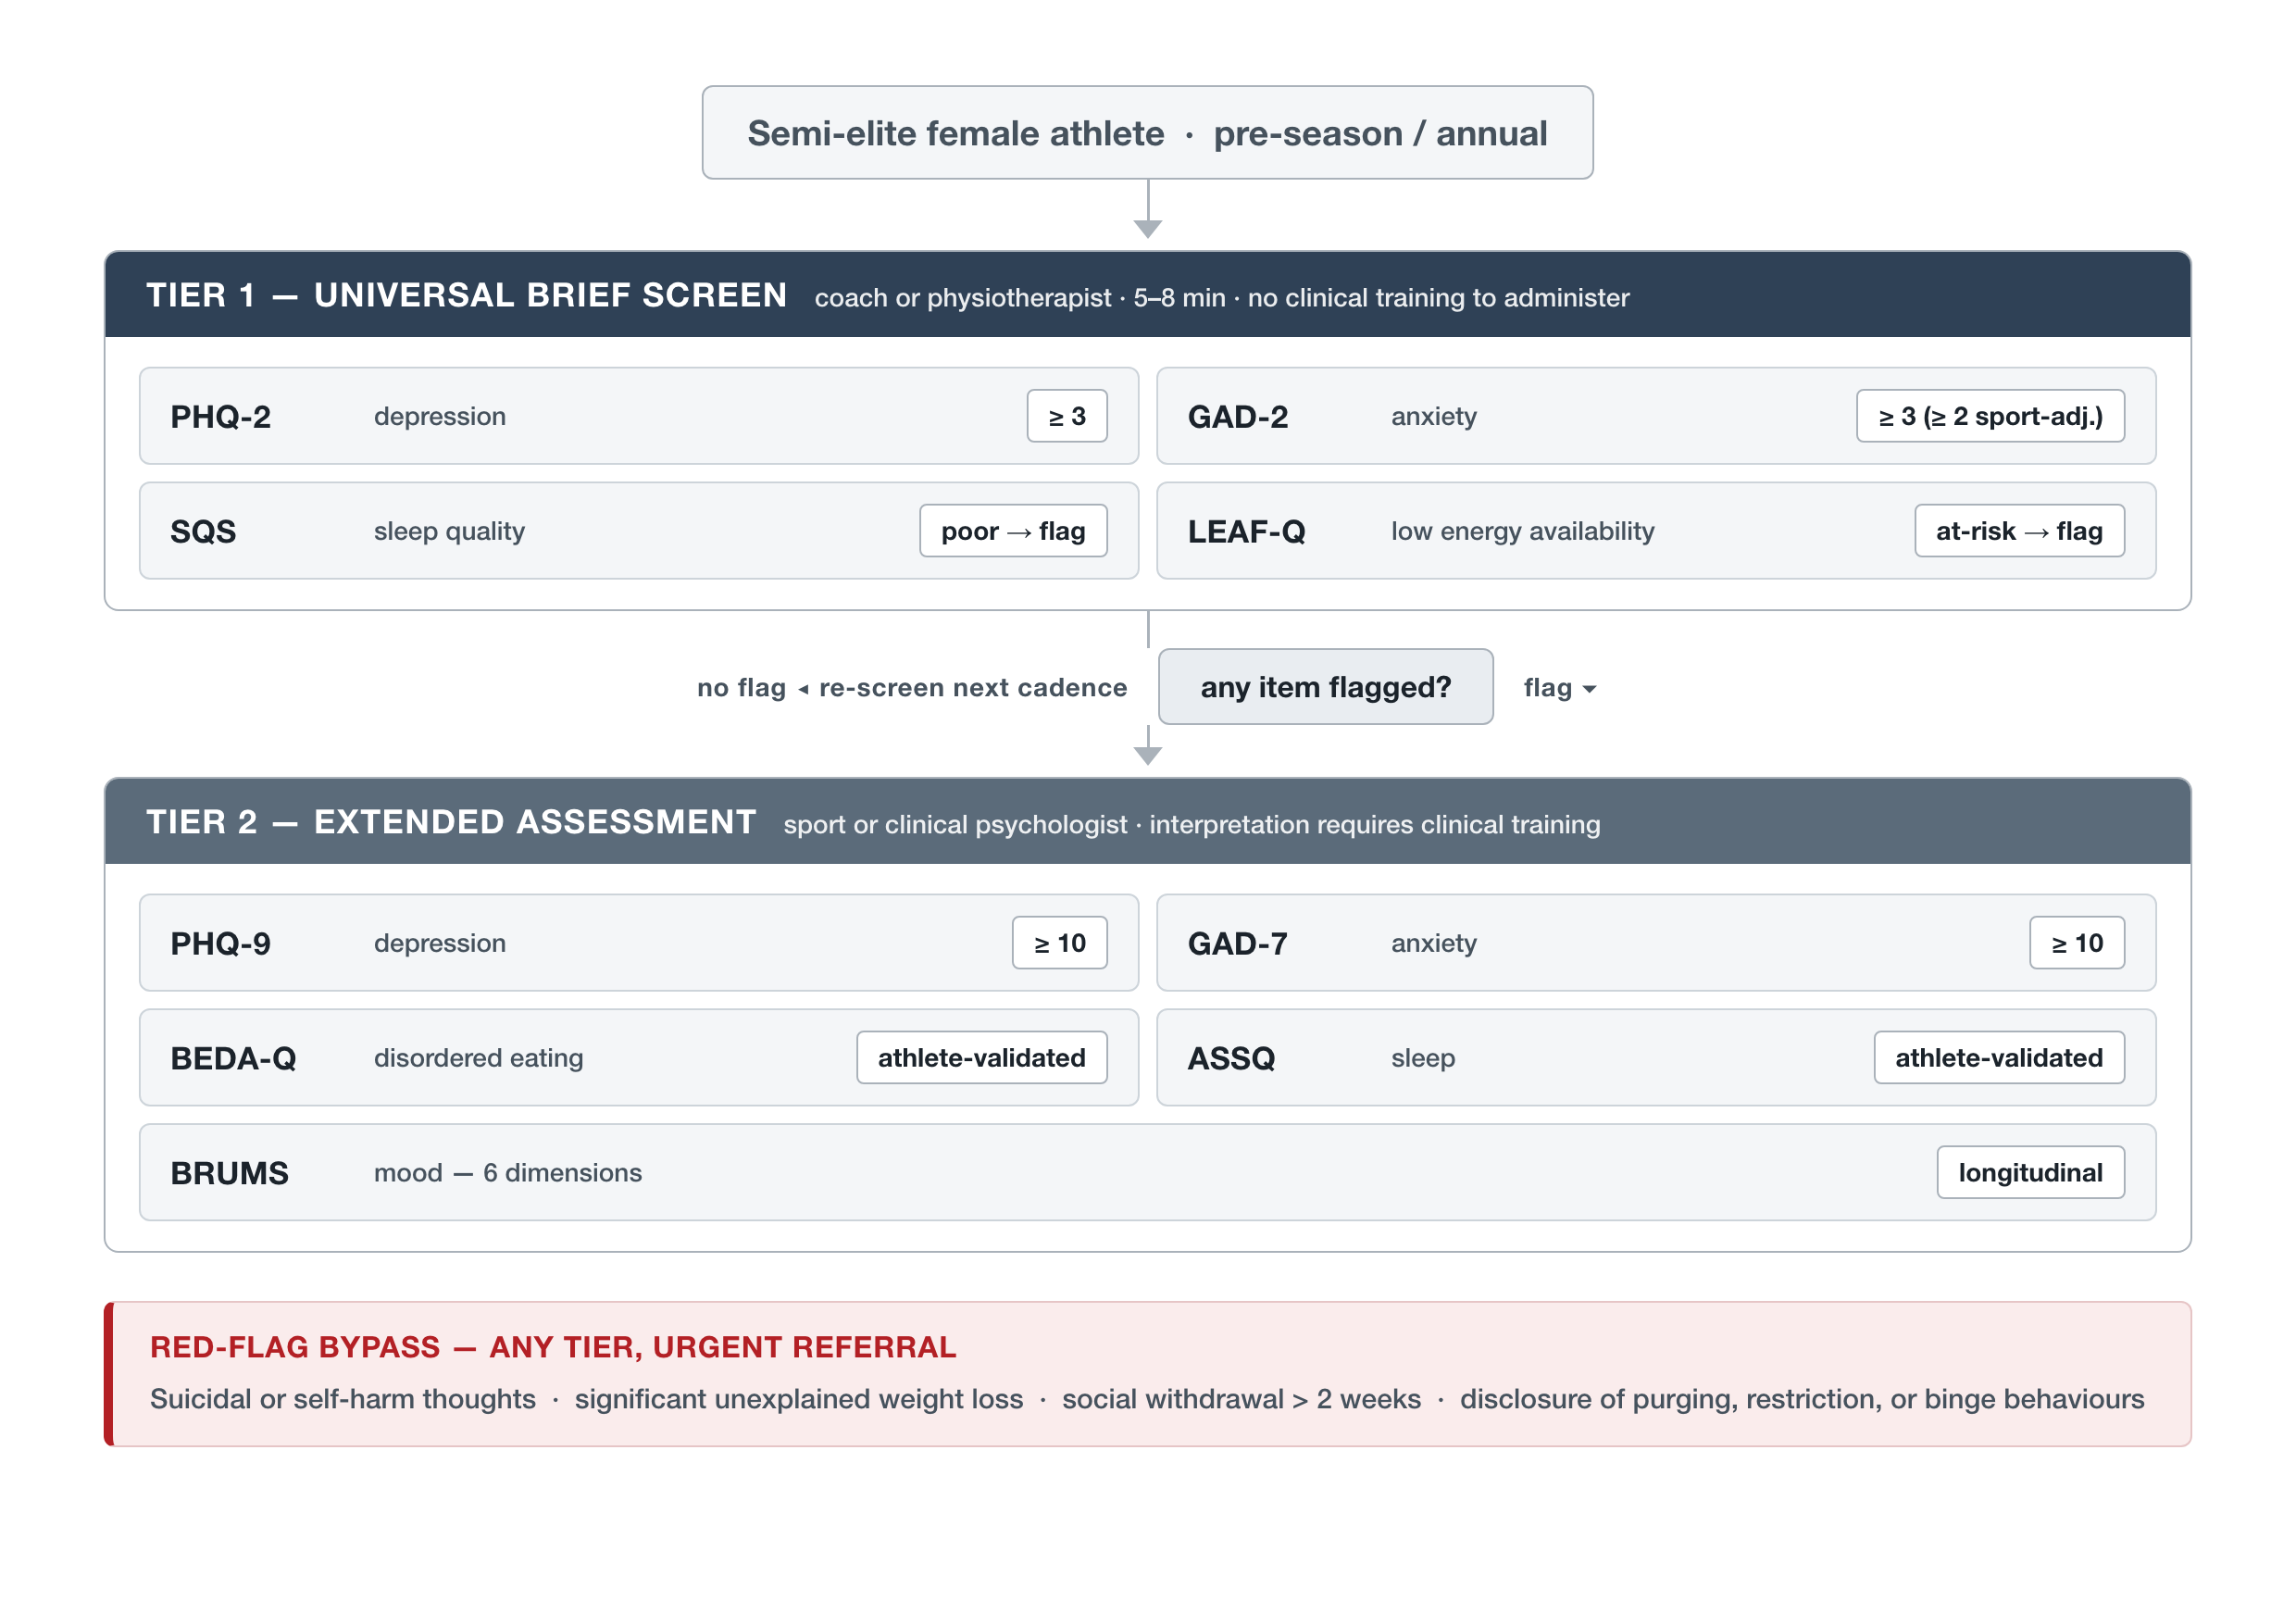
Tier 1 is a brief, universal screen a coach or physiotherapist can administer in five to eight minutes without clinical training (the Patient Health Questionnaire-2, the Generalized Anxiety Disorder-2, the Single-Item Sleep Quality Scale, and the Low Energy Availability in Females Questionnaire); any flagged item triggers Tier 2 extended assessment by a sport or clinical psychologist (the Patient Health Questionnaire-9, the Generalized Anxiety Disorder-7, the Brief Eating Disorder in Athletes Questionnaire, the Athlete Sleep Screening Questionnaire, and the Brunel Mood Scale). The red-flag indicators shown warrant urgent referral regardless of tier. The two-tier structure adapts the IOC Sport Mental Health Assessment Tool-1 (SMHAT-1) to a low-resource setting(8). These tools are validated in the indicated populations(9-15).
Referral Pathways
A screening result is clinically useful only if it connects to action. Historically, sports medicine has relied on the ‘cold referral’, in which a practitioner hands a distressed athlete a phone number or directory and expects her to initiate contact independently. This passive approach asks the most of the athlete at the point when depression and anxiety most impair the motivation and executive function needed to follow through.
Referral Pathway for Semi-Elite Settings
- Step 1: Tier 1 screen flags concern: Document the result. Do not attempt to manage it within the coaching or physiotherapy role.
- Step 2: Warm referral: The practitioner personally introduces the athlete to the next provider rather than handing over a contact; this aims to reduce the logistical and motivational friction that often prevents a distressed athlete from following through. Warm referrals lead to higher engagement with behavioral health services(16-18).
- Step 3: Feedback loop: With athlete consent, the referring practitioner receives a brief outcome summary. This keeps psychological health integrated with physical monitoring rather than siloed in a separate clinical stream.
- Step 4: Document and track: Screening results, referral dates, and outcomes should be recorded alongside physical health data. A single data point shows the present situation; a trend shows the trajectory.
Timing And Frequency
Screening is most useful as a repeated measure, not a one-off. A single Tier 1 screen captures a moment; a season of brief, regular screens captures a trajectory, which is what allows a practitioner to distinguish a transient dip from a developing problem.
A workable cadence for a semi-elite season mirrors the rhythm of physical monitoring. A full Tier 1 screen at pre-season establishes a baseline before training load and competition pressure build. A brief in-season check, the PHQ-2 and GAD-2 alone, repeated every four to six weeks or after a major stressor such as injury, deselection, or a heavy competition block, flags emerging concerns while they are still manageable. A final screen at the end of the season captures the off-season transition, a period of elevated risk as structure, identity, and routine fall away.
The aim is not to add a burden but to fold two minutes of psychological monitoring into existing contact points. An athlete who completes a brief screen alongside her routine blood work or load monitoring is far more likely to engage than one asked to attend a separate appointment.
“Screening is most useful as a repeated measure, not a one-off.”
The Stigma Problem
A screening framework addresses the structural barrier. It does not address stigma, but practitioners are not powerless here either. The language used around psychological screening matters. Framing screening as ‘performance optimization’ rather than ‘mental-illness detection’ may improve the help-seeking calculus for athletes who would otherwise disengage, and current frameworks endorse this framing to reduce stigma, though direct comparative data on how different framings affect disclosure rates remain limited(19).
Practical steps that shift the culture without requiring structural change: normalize the conversation by discussing psychological screening in the same breath as blood work during pre-season orientation; use the word ‘monitoring’ rather than ‘assessment’ when describing the process to athletes; and make Tier 1 screening universal rather than targeted at athletes who appear to be struggling, which removes the stigma of being singled out.
Connecting The Dots
Psychological screening is the third dimension this series has examined in depth, following menstrual cycle monitoring (Part I) and blood biomarker screening (Part II). These three are not a collection of independent checklists, and they are not the finished picture either. They are the first domains of a broader screening framework this series is building dimension by dimension, and each already generates information relevant to the others.
An athlete with heavy menstrual bleeding and low ferritin (Parts I and II) is at elevated risk for psychological symptoms via the fatigue and cognitive-impairment pathways of iron deficiency. An athlete whose cortisol and thyroid markers suggest energy deficiency (Part II) warrants a LEAF-Q screen (Part III). An athlete whose psychological screen reveals disordered eating cognition warrants immediate re-examination of her iron and hormonal panel.
Consider a concrete case. A hypothetical 19-year-old distance runner returns three individually borderline results: a borderline-low ferritin, a LEAF-Q score above threshold, and a GAD-2 of two. Each is easy to dismiss alone, but read together they describe low energy availability driving both iron dysregulation and anxiety, yielding a single actionable referral weeks before any individual marker would cross a threshold on its own. The figure is an illustrative composite, not a specific patient (see figure 3)(10,12).

Practitioners who implement these three components are not running three separate programs. They are building one integrated health monitoring system, one dimension at a time, which is precisely what the semi-elite female athlete has always needed and rarely had access to.
“The instruments are validated, brief, and freely available.”
Summary
Psychological screening is not a specialist activity reserved for clinical psychologists. For semi-elite female athletes, it is a two-minute Tier 1 process that any coach or physiotherapist can administer, with a clear referral pathway when results warrant it. The evidence connecting psychological distress to physical performance outcomes is consistent. The instruments are validated, brief, and freely available. What has been missing is the framework and a willingness to treat mental health as a non-negotiable component of athlete care rather than an optional add-on for athletes who visibly struggle.
The semi-elite female athlete deserves the same systematic approach to her psychological health that her physical health is increasingly receiving. The tools are ready. The gap is a choice.
Practical Resources for Coaches and Practitioners
- PHQ-2/PHQ-9 and GAD-2/GAD-7: Freely available at phqscreeners.com.
- LEAF-Q: Available via British Journal of Sports Medicine supplementary materials.
- BRUMS: Available through Human Kinetics and validated sport psychology resources.
- Sport England Mental Health in Sport toolkit: Practitioner-facing guidance for non-clinical staff.
References
1. J Athl Train. 2023;58(9):715-721.
2. J Athl Train. 2016;51(5):389-397.
3. J Appl Sport Psychol. 1998;10(1):5-25.
4. Sports Med. 2016;46(9):1333-1353.
5. Br J Sports Med. 2023;57(17):1073-1097.
6. BMC Psychiatry. 2012;12:157.
7. Br J Sports Med. 2021;55(7):356-368.
8. Br J Sports Med. 2021;55(1):30-37.
9. Med Care. 2003;41(11):1284-1292.
10. Sport Psychol. 2020;34(4):300-309.
11. J Clin Sleep Med. 2018;14(11):1849-1857.
12. Br J Sports Med. 2014;48(7):540-545.
13. Med Sci Sports Exerc. 2014;46(8):1666-1675.
14. Sports Med Open. 2018;4(1):23.
15. J Sports Sci. 1999;17(11):861-872.
16. Ann Fam Med. 2018;16(4):346-348.
17. J Adolesc Health. 2023;73(2):325-330.
18. J Pediatr Health Care. 2025;39(3):396-407.
19. Sports Psychiatry. 2025;4(3):167-172.

Latest Issue

Subscribe Today
Newsletter Sign Up
Subscriber Testimonials
Dr. Alexandra Fandetti-Robin, Back & Body Chiropractic
Elspeth Cowell MSCh DpodM SRCh HCPC reg
William Hunter, Nuffield Health
Subscribe Today




Newsletter Sign Up




Coaches Testimonials
Dr. Alexandra Fandetti-Robin, Back & Body Chiropractic
Elspeth Cowell MSCh DpodM SRCh HCPC reg
William Hunter, Nuffield Health
Subscribe Today
Latest Issue

Be at the leading edge of sports injury management
Our international team of qualified experts (see above) spend hours poring over scores of technical journals and medical papers that even the most interested professionals don't have time to read.
For 17 years, we've helped hard-working physiotherapists and sports professionals like you, overwhelmed by the vast amount of new research, bring science to their treatment. Sports Injury Bulletin is the ideal resource for practitioners too busy to cull through all the monthly journals to find meaningful and applicable studies.
*includes 3 coaching manuals
Get Inspired
All the latest techniques and approaches


Sports Injury Bulletin brings together a worldwide panel of experts – including physiotherapists, doctors, researchers and sports scientists. Together we deliver everything you need to help your clients avoid – or recover as quickly as possible from – injuries.
We strip away the scientific jargon and deliver you easy-to-follow training exercises, nutrition tips, psychological strategies and recovery programmes and exercises in plain English.
